

Tumors are often described as being stiffer than the tissue around them. Measuring that stiffness inside a living organism, though, is not as simple as pressing on the tissue and reading out a modulus.
Imaging can show how a tumor deforms under load, while direct mechanical testing can provide a more conventional measurement of stress, strain, and Young’s modulus. Bringing those two approaches into agreement is where tumor stiffness measurement becomes more interesting.
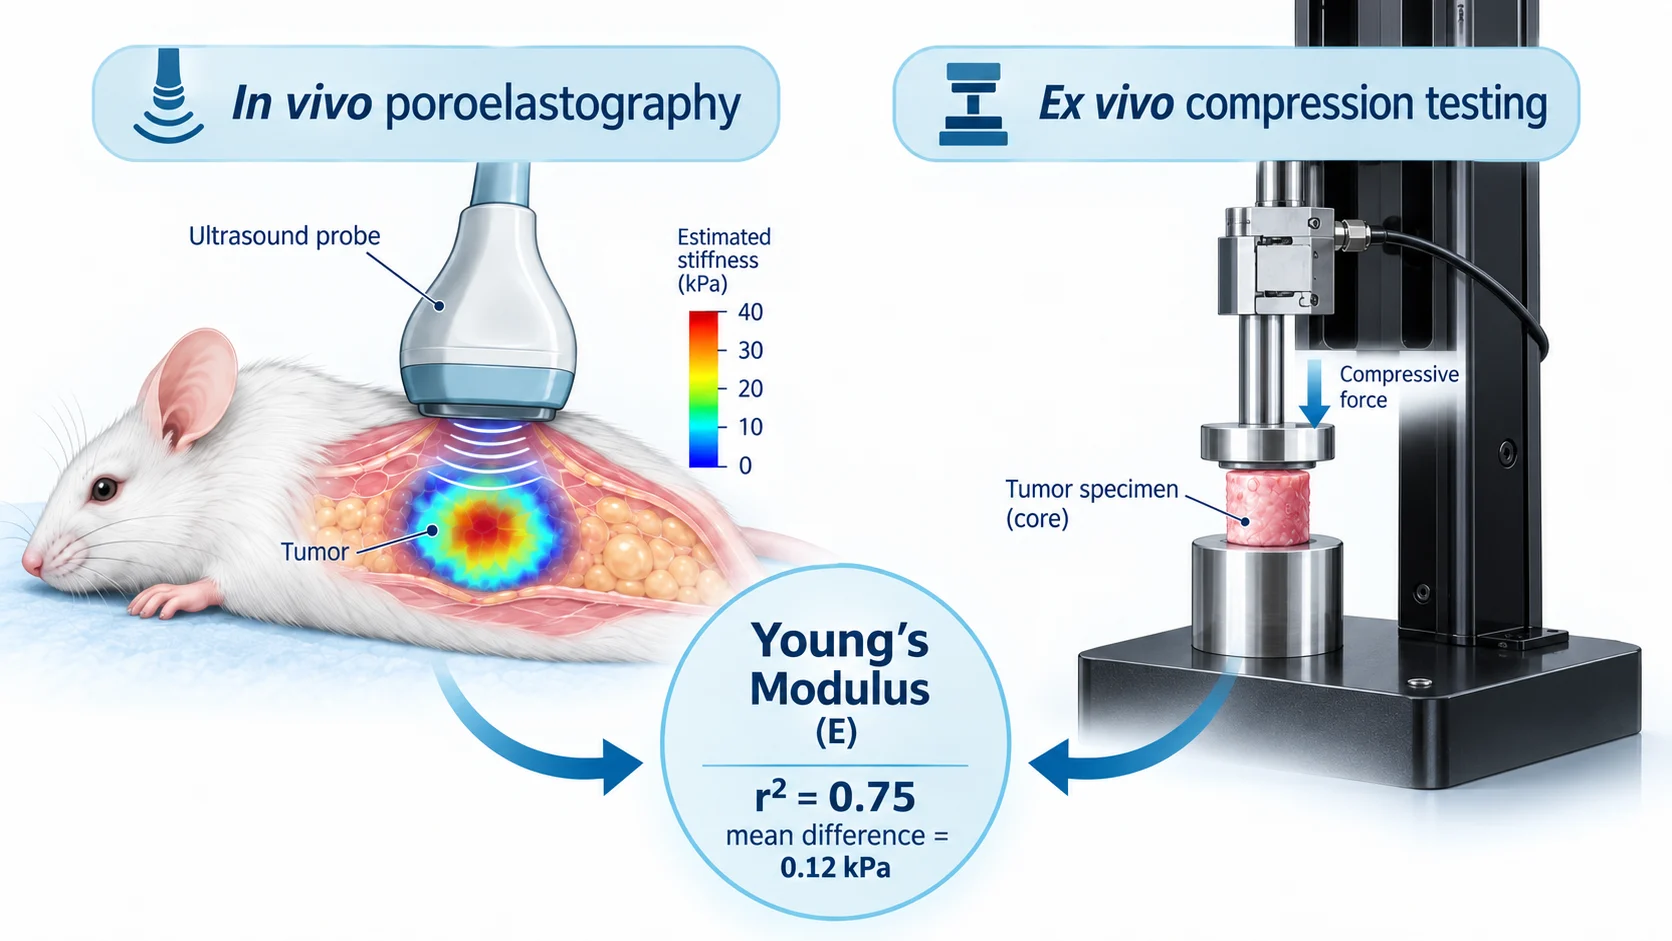
A 2026 study published in Scientific Reports by researchers our of Texas A&M University, Stanford University, and Houston Methodist Research Institute looked at this problem using ultrasound poroelastography. The researchers estimated Young’s modulus in breast cancer xenografts in vivo, then removed samples from the same tumors and tested them mechanically. A CellScale UniVert was used for the ex vivo compression testing, giving the researchers an independent mechanical measurement to compare with the imaging-based estimate.
The study sits at an interesting intersection of cancer mechanobiology, elastography, and soft tissue mechanics. It also gets at a practical question that comes up whenever stiffness is inferred through imaging: if the imaging method gives you a number, how do you check whether that number reasonably represents the mechanical behaviour of the tissue?
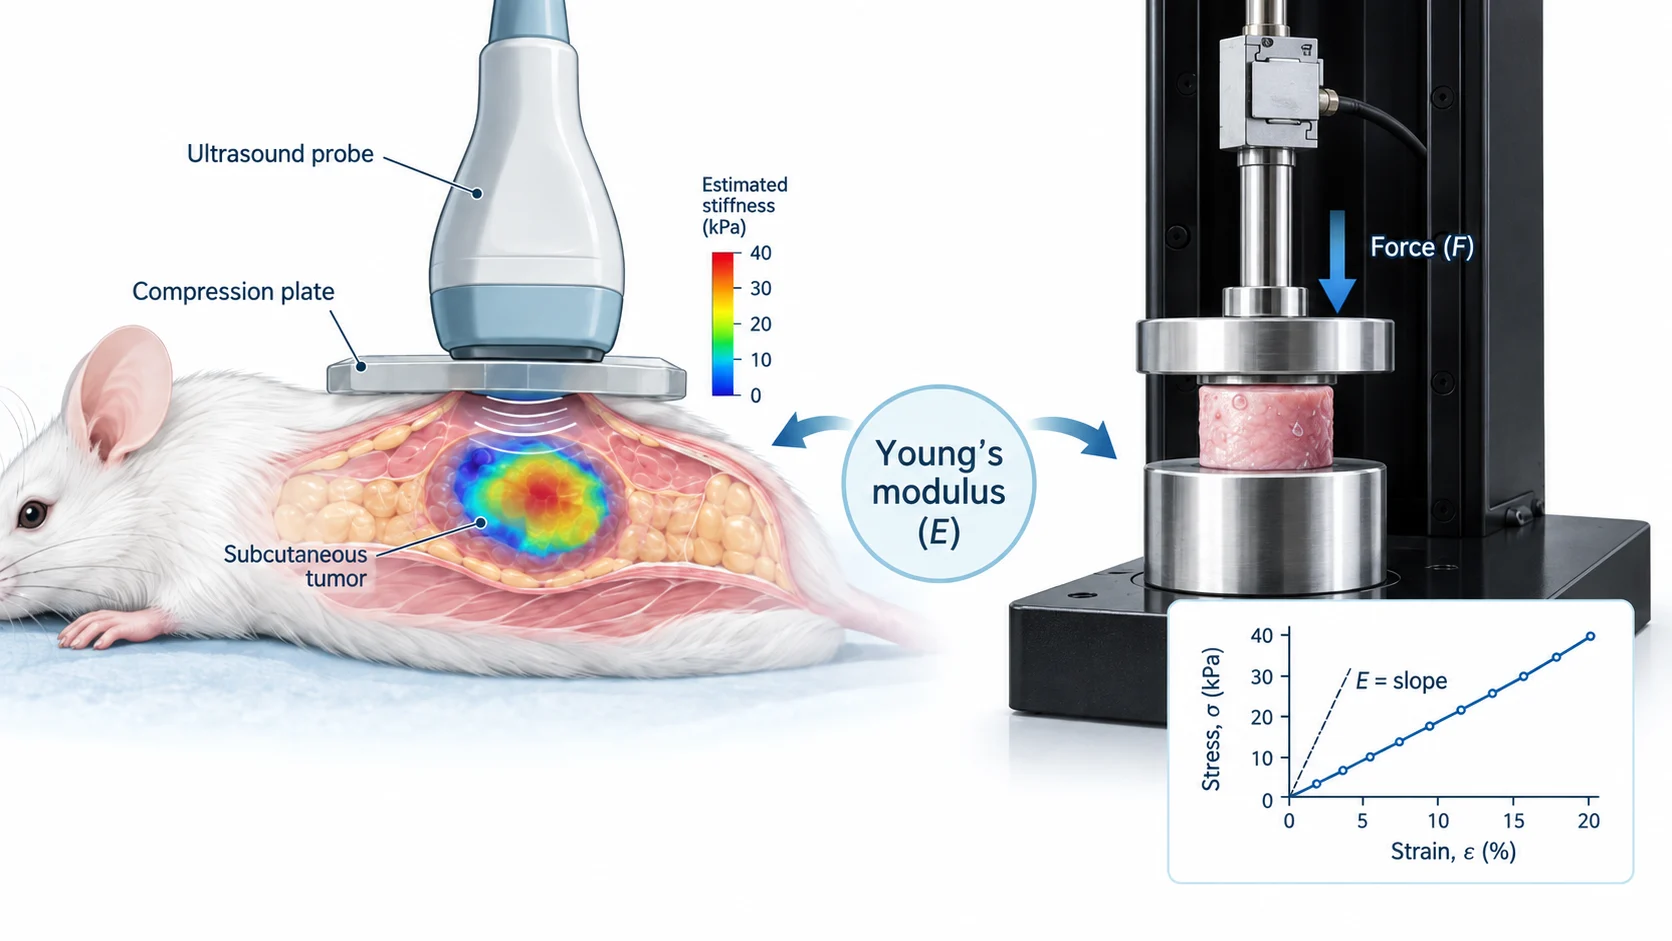
Why Tumor Stiffness Measurement Is Difficult in Living Tissue
Young’s modulus is commonly used to describe how resistant a material is to deformation. With a simple elastic material, the idea is fairly direct. Biological tissues are less cooperative.
Tumors contain cells, extracellular matrix, blood vessels, and interstitial fluid. When a tumor is compressed, the solid structure deforms while fluid can move through the tissue. The measured response therefore changes with time. For tumor stiffness measurement, that means assumptions that work reasonably well for an elastic solid may not hold for a fluid-rich, poroelastic tissue.
This matters in cancer mechanobiology, where tissue stiffness is increasingly considered alongside extracellular matrix remodeling, cell behaviour, tumor growth, and transport through the tumor microenvironment. The paper discusses ECM deposition and cross-linking as processes associated with increasing stiffness, along with links between tissue mechanics and proliferation, migration, invasion, and drug transport.
A previous study approached this from the biological side, looking at how cancer-associated fibroblasts and collagen remodeling can affect tumor stiffness. The new study asks something different: How can tumor stiffness measurement be performed noninvasively, and how closely does that estimate agree with direct mechanical testing afterward?
Why Poisson's Ratio Matters in Ultrasound Elastography
Many ultrasound elastography methods simplify the problem by treating soft tissue as nearly incompressible, often using a Poisson’s ratio close to 0.5.
The authors point out that this assumption does not necessarily hold for poroelastic tissues. They cite reported Poisson’s ratios across a considerably wider range for fluid-rich soft tissues. At the same time, lateral strain is generally harder to measure accurately with conventional ultrasound than axial strain. Both issues can affect reconstruction of Young’s modulus.
Their approach uses a poroelastic correction to improve the lateral strain estimate, then applies Eshelby’s inclusion theory to estimate both Young’s modulus and Poisson’s ratio rather than fixing Poisson’s ratio in advance.
The simulation work gives some indication of why that matters for tumor stiffness measurement. When the reconstruction instead assumed a Poisson’s ratio of 0.5, error in the estimated Young’s modulus increased as the true Poisson’s ratio fell. The difference became statistically significant when the simulated true value was below 0.40.
How Did the Researchers Perform Tumor Stiffness Measurement In Vivo?
The animal portion of the study used 15 mice with orthotopic MDA-MB-231 breast cancer xenografts. The tumors were grouped by volume as small, medium, or large before imaging.
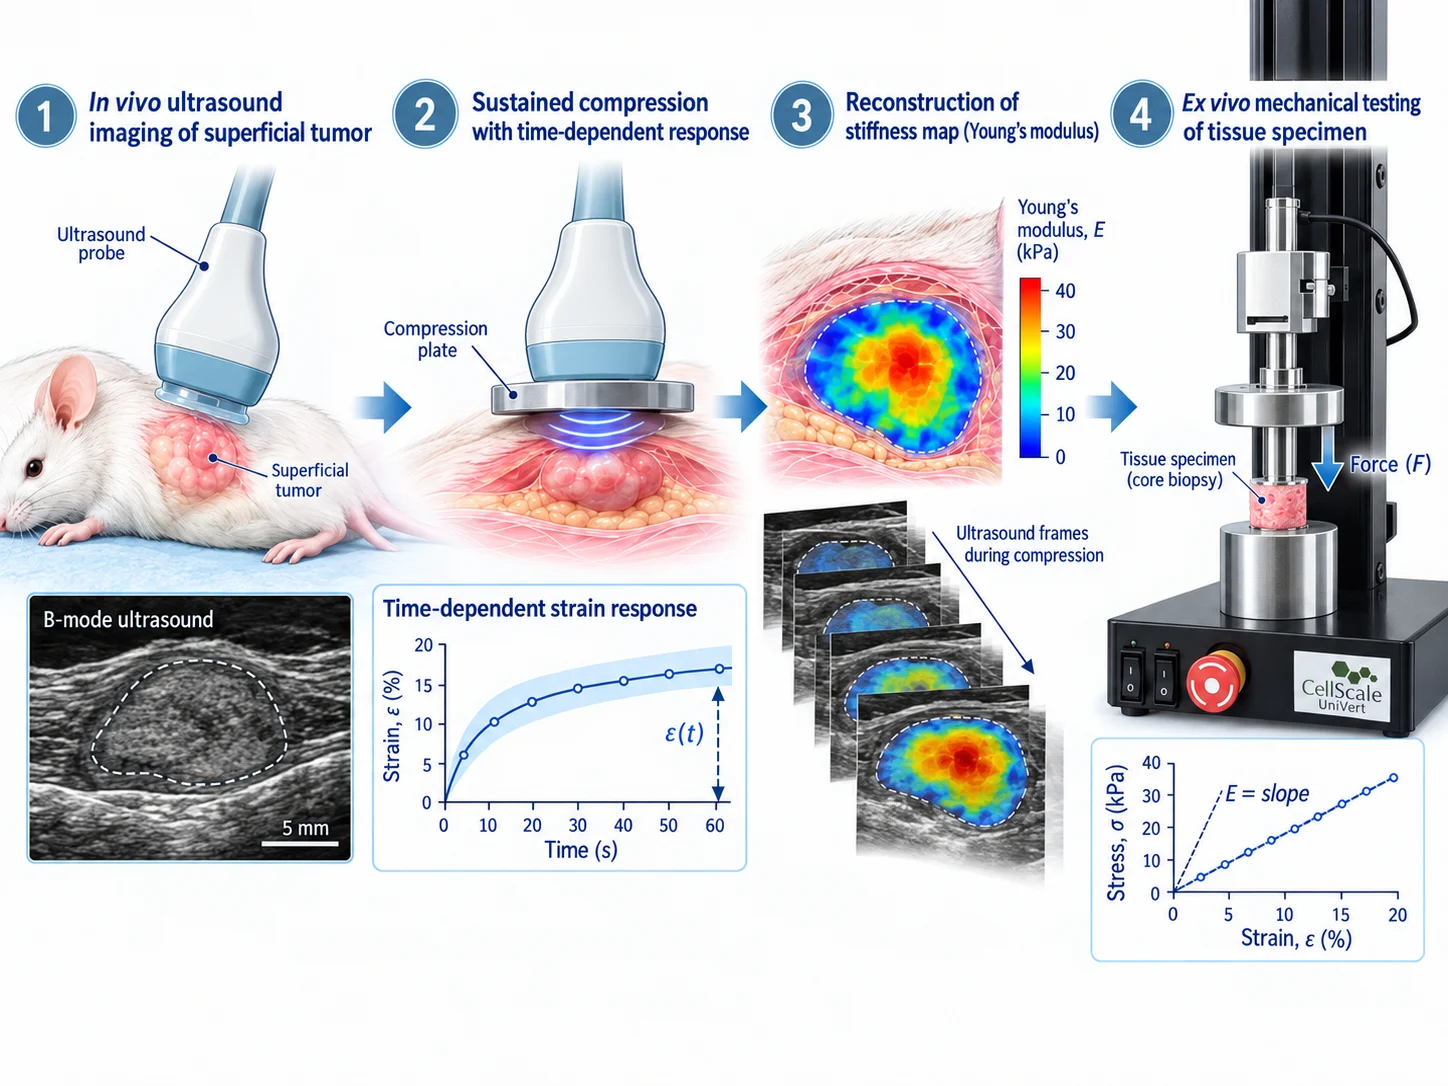
For the in vivo tumor stiffness measurement, ultrasound radiofrequency data were collected while a compressor plate applied load to the superficial tumor. A gel pad was positioned between the plate and the tissue.
Compression was maintained for 60 seconds while ultrasound frames were acquired at 10 frames per second. The applied force was measured separately, while the ultrasound data were used to follow deformation within the tissue.
This is closely related to a creep testing type of loading condition. The load remains applied while the tissue response changes with time.
Following a Poroelastic Tissue Toward Steady State
That time component is central to the method.
Immediately after compression, pressure within the fluid phase contributes to the response. As fluid redistributes, the tissue moves toward a more relaxed condition. The authors argue that Young’s modulus should be estimated using the fully relaxed, or drained, response rather than the initial undrained response. Using the instantaneous strain can otherwise produce a higher modulus estimate in poroelastic tissue.
For tumor stiffness measurement, the deformation history therefore contains useful information rather than simply being something to average out.
The ultrasound data were processed to estimate axial and lateral strains. After applying the poroelastic lateral-strain correction, the researchers used the steady-state strain information, applied stress, and tumor geometry to reconstruct Young’s modulus and Poisson’s ratio.
One advantage of the imaging approach is that the result is spatial. Instead of reducing an entire tumor to one stiffness number, the method can reconstruct a map of Young’s modulus across the imaged region.
How the UniVert Supported Tumor Stiffness Measurement
Once the imaging experiments were complete, the researchers moved from an indirect stiffness estimate to a physical mechanical test.
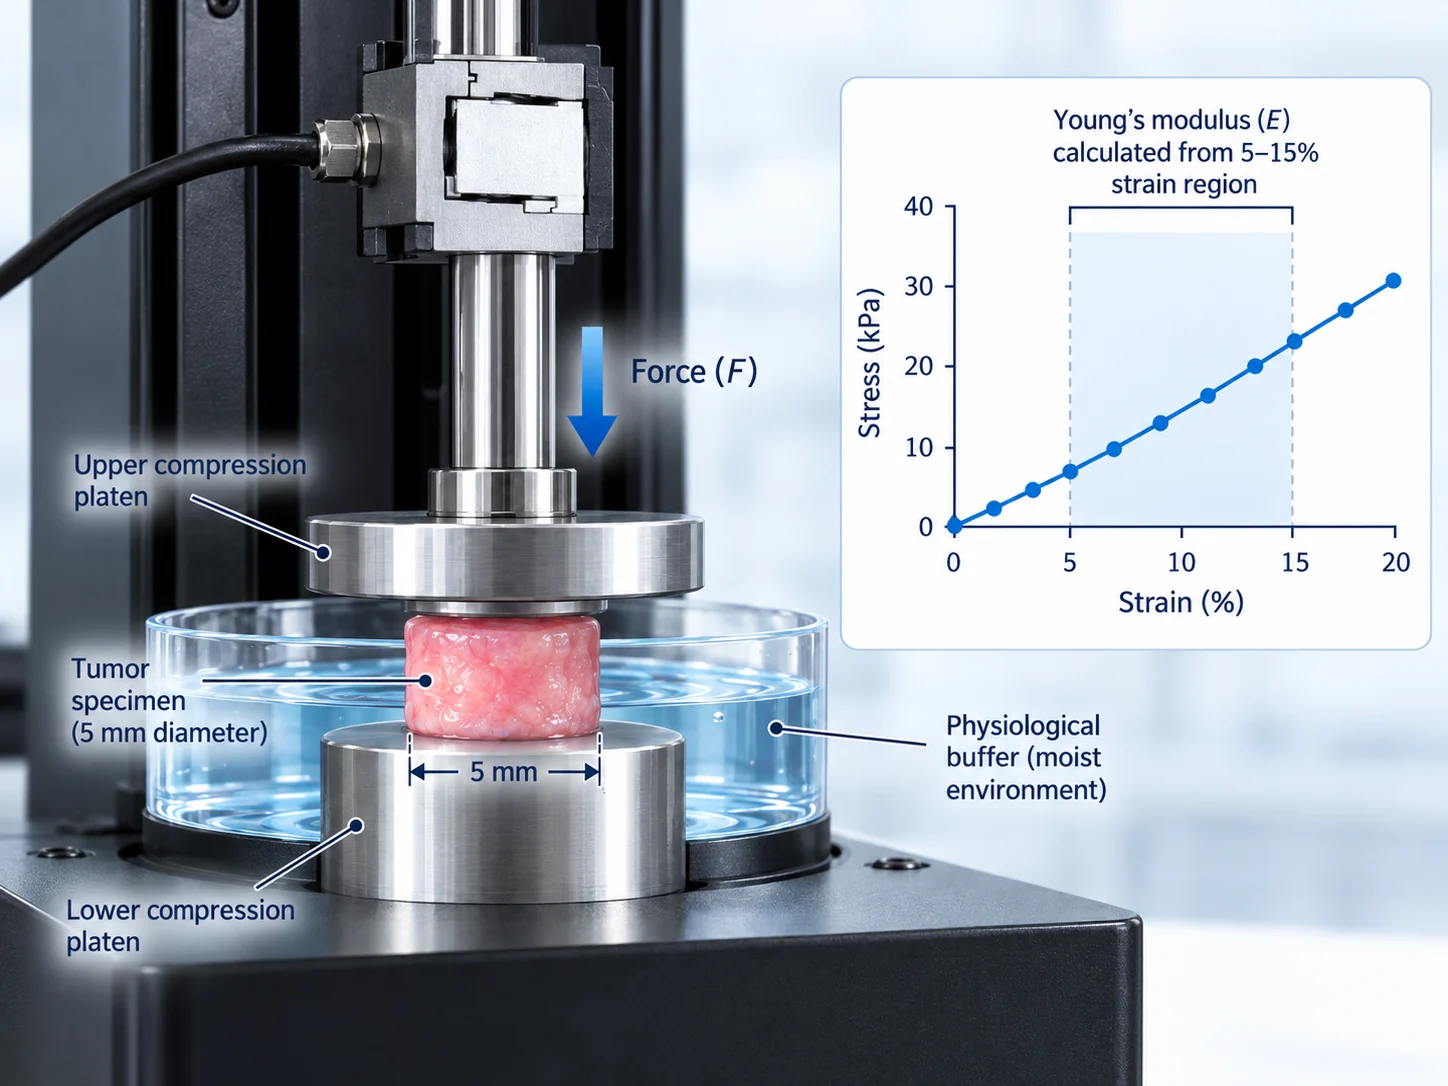
The tumors were excised and 5 mm diameter specimens were removed with a biopsy punch. The samples were flash frozen, stored at -80°C, then thawed in warm phosphate-buffered saline before testing. Excess surface moisture was gently removed before the mechanical measurements.
The researchers then used a UniVert mechanical tester for uniaxial compression testing.
A 10 N load cell was used. Initial contact with the sample was identified at a measured force between approximately 0.04 and 0.06 N. The specimens were then tested with a displacement magnitude of 50% over a total duration of 120 seconds, including a 5 second relaxation period.
This mechanical step is what turns the paper from an imaging-only study into an experimental validation study. The UniVert measurements provided a separate route to tumor stiffness measurement, based directly on measured force and specimen deformation.
Matching the Mechanical Test to the Imaging Strain Range
The researchers generated stress-strain curves from the UniVert data and calculated Young’s modulus from a linear fit between 5% and 15% strain.
That window was chosen deliberately. The strains produced during the in vivo poroelastography experiments were also in the 5% to 15% range.
Looking across the complete mechanical curves, which extended to 50% strain, the tumors showed a nonlinear response. Within the narrower 5% to 15% interval, however, the stress-strain relationship was reasonably linear.
For tumor stiffness measurement, that matching is worth paying attention to. An imaging-derived modulus obtained at relatively small deformation would not necessarily be directly comparable with a mechanical modulus calculated over a very different portion of a nonlinear stress-strain curve.
Here, the authors tried to keep the comparison on similar mechanical footing.
There is a parallel with another study on validating AI-based elastography measurements. That work used a different elastography approach and different specimens, but direct compression testing again provided an independent mechanical reference for an imaging-derived measurement.
Why Compression Testing Instead of Indentation?
The authors also discuss why they chose bulk compression rather than indentation testing for the ex vivo comparison.
Indentation can be less sensitive to larger surface irregularities, but it probes a more localized region. The authors note that the limited penetration depth in their specimens, less than 100 µm, would not fully sample the tissue volume. Half-space and homogeneity assumptions could also become problematic in tumors containing necrotic or calcified regions.
Compression gave them a bulk-averaged mechanical property that could be compared with the average modulus obtained from the imaging data.
That does not mean compression is always the better method for tumor stiffness measurement. It means it fit the particular comparison being made here.
How Closely Did the Tumor Stiffness Measurements Agree?
This comparison is the part of the study that makes the UniVert measurements particularly relevant.
For each of the 15 tumors, Young’s modulus estimated in vivo using poroelastography was compared with Young’s modulus obtained from the ex vivo mechanical test. Across the samples, the two sets of tumor stiffness measurements had a coefficient of determination of r² = 0.75.
The abstract reports a percentage relative error below 15% for most experimental cases. Later in the discussion, the authors describe the average percentage error between the in vivo and ex vivo estimates as below 20%. Those statements describe the data in slightly different ways, so it is useful not to collapse them into a single number.
A Bland-Altman analysis gave a mean difference between mechanical testing and poroelastography of 0.12 kPa, with 95% limits of agreement of approximately -38 to +38 kPa. The average bias was small, although the relatively broad limits show that individual measurements could still differ appreciably.
For an experimental tumor stiffness measurement method, that distinction matters. A strong overall relationship does not mean every imaging estimate exactly reproduces the mechanical result.
Tumor Size Showed a Trend, Not a Significant Difference
Both approaches showed a general increase in mean Young’s modulus as tumors increased in size. The researchers did not find statistically significant differences between the small, medium, and large groups.
The sample sizes were also uneven and relatively small: 3 small tumors, 4 medium tumors, and 8 large tumors.
Mechanical variability between tumors is not particularly surprising. Nor does one part of a tumor necessarily represent another.
An earlier study on prostate cancer xenograft stiffness looked at this problem from the direct mechanical-testing side, measuring stiffness across tumor specimens and regions. That makes a useful companion to the current study, where poroelastography can produce spatial information but the ex vivo validation is reduced to a bulk modulus.
What Can Affect Tumor Stiffness Measurement When Comparing In Vivo and Ex Vivo Data?
Perfect agreement would probably be surprising, because the tumor is not mechanically identical before and after excision.
Interstitial fluid pressure changes once tissue is removed from the body, while some growth-induced solid stress may remain. The authors discuss these changes as one possible reason why the in vivo and ex vivo tumor stiffness measurements do not match exactly.
Sample preparation adds another layer. The specimens were flash frozen and later thawed before testing. The researchers used controlled rehydration in PBS, but preservation, handling, and testing conditions are still part of what a measured modulus represents.
There is also a difference in scale. Poroelastography reconstructs Young’s modulus on a pixel-by-pixel basis. Compression testing gives a bulk mechanical response for the specimen. In heterogeneous tumor tissue, those are related measurements, but they are not measuring the tissue in exactly the same way.
Another issue is the material model. The full mechanical curves were nonlinear, but Young’s modulus was calculated from the approximately linear 5% to 15% region. The authors acknowledge that linear elasticity has limitations here and suggest that future work could explore more advanced models such as hyperelastic formulations.
These are familiar considerations across tissue engineering and soft tissue biomechanics. Strain range, loading history, specimen geometry, hydration, preservation, and measurement scale can all change what a stiffness value actually describes.
For tumor stiffness measurement, simply reporting a Young’s modulus without those details can leave out quite a lot of the experiment.
Where Tumor Stiffness Measurement Fits Within Cancer Mechanobiology
One thing that stands out in this study is that tumor stiffness measurement is not being treated only as a material-characterization problem.
The longer-term aim is to estimate mechanical properties while the tissue remains in the body. If quantitative elastography can provide a reasonable estimate of tumor Young’s modulus in vivo, researchers could potentially follow mechanical changes over time while retaining the native tumor environment.
That could be useful when studying tumor growth, extracellular matrix remodeling, or responses to treatment. This particular study did not test treatment effects, so those applications remain possibilities rather than outcomes of the current experiments.
Other studies approach the tumor microenvironment from different directions. The work on tumor stiffness and cancer-associated fibroblasts looks more closely at how cellular and collagen changes contribute to mechanics. Another study used mechanical characterization while developing a 3D bioprinted osteosarcoma model for drug testing.
The current paper adds another piece to that picture. Here, direct mechanical testing acts as the reference for an attempt to move tumor stiffness measurement into the living tissue itself.
There are still reasons to be cautious. The study used 15 animals and one triple-negative breast cancer cell line. The results do not show that the same agreement will necessarily occur for other cancers, tumor geometries, or clinical measurements.
What the experiment does provide is a direct comparison between an in vivo estimate and mechanical testing of tissue taken from the same tumors.
Using the UniVert for Tumor Stiffness Measurement and Soft Tissue Compression Testing
The UniVert is a uniaxial mechanical testing system used to characterize biomaterials and biological tissues under controlled loading.
In a compression experiment like the one in this study, a specimen is placed between platens while force and displacement are recorded. With appropriate specimen dimensions, those measurements can be converted into stress and strain and used to examine properties such as stiffness or Young’s modulus.
The useful part for soft biological materials is that the loading protocol can be built around the mechanical question being asked. Alongside monotonic compression, researchers may use cyclic loading, creep, stress relaxation, and other approaches depending on the tissue or material. The system can also be configured for other forms of soft materials testing when the specimen or research question changes.
For tumor stiffness measurement in this study, the UniVert had a much narrower role. It was used to compress the excised specimens and produce the stress-strain data from which a bulk Young’s modulus could be calculated.
Those measurements then served as the independent mechanical reference for the poroelastography estimates.
That relationship is what makes the work interesting from a mechanical-testing perspective. The imaging technique is being developed because the researchers ultimately want stiffness information without removing the tissue. But to evaluate that new approach, they still needed to put a physical sample under load and measure how it actually responded.
For tumor stiffness measurement, the two approaches are not really competing here. One is helping establish confidence in the other.
Source Publication
Khan, M.H.R., Islam, M.T., Majumder, S. et al. First demonstration of in vivo estimation of Young’s modulus in cancers using poroelastography with experimental validation. Sci Rep (2026). https://doi.org/10.1038/s41598-026-70125-0